

AACR 2026: David Parkinson and the Arc of Modern Cancer Therapy

SAN DIEGO, CA – In 1977, when David R. Parkinson, MD, graduated from medical school at the University of Toronto and moved to McGill University to train in internal medicine and eventually hematology, the idea of medical oncology was in its infancy. In Canada, the profession didn’t exist.

“In Canada, there were no medical oncologists,” Parkinson told Inside Precision Medicine. “Radiation therapists administered what little chemotherapy existed. They resisted the development of medical oncology as a specialty.”

David Parkinson - AACR
David R. Parkinson, MD, recipient of the 2026 AACR Outstanding Achievement Award for Service to Cancer Science and Medicine [The American Association for Cancer Research (AACR)]

Through the ensuing 49 years, Parkinson didn’t just see the rise of kinase inhibitors, antibodies, and cell therapies in real-time—he helped create the world of modern cancer therapeutics.

In reflecting on his remarkable career, which was recognized with the 2026 AACR Outstanding Achievement Award for Service to Cancer Science and Medicine, Parkinson said, “I’ve essentially grown alongside the field.”

From scarcity to structure: Oncology’s early years

When Parkinson arrived in Montreal, there were only a handful of chemotherapeutics available. “In those days, there were only one or two drugs available for hematologic malignancies across the entire field,” Parkinson said. “The main treatments were cyclophosphamide and nitrosoureas.”

Even supportive care lagged. “Initially, we had no effective way to control chemotherapy-induced nausea,” he noted of the standard of care for testicular cancer. “Some patients stopped treatment because they couldn’t tolerate it.”

Parkinson explained that early cancer drugs worked best on rapidly dividing tumors, like leukemias and testicular cancers, because that’s what the animal models represented. These therapies targeted DNA and cell division broadly, often with severe toxicity, and were far less effective against slower-growing solid tumors.

After his residency at McGill, Parkinson moved to Boston, first to Tufts New England Medical Center on a modest Canadian fellowship that placed him at the edge of a field just beginning to coalesce. “I was on a Canadian fellowship earning $12,000 a year,” he said. “The exchange rate fluctuated significantly, which made things difficult, and I couldn’t work due to my student visa.”

What he found, however, was momentum. Through connections with Dana-Farber, Parkinson entered formal training in medical oncology as the specialty began to take shape. “I connected with Dana-Farber and took their introductory course for fellows—that was my entry into medical oncology.”

At the same time, breakthroughs in specific cancers hinted at what might be possible. “What really shaped my thinking was the emergence of treatments for testicular cancer just as I entered oncology,” he said. “Platinum-based therapies—and later combination regimens—felt like miracles. We had never seen anything like it. These were often young patients, difficult to manage, but suddenly there were real cures.”

Targeted therapy and the Gleevec moment

Parkinson’s career soon intersected with early efforts to harness the immune system against cancer—decades before immunotherapy became a dominant paradigm. “I became deeply involved in immunotherapy, particularly interleukin-2 and early tumor-infiltrating lymphocyte studies,” he said.

Working at the National Cancer Institute (NCI), he collaborated with leaders, including immunotherapy pioneer Steven Rosenberg, MD, PhD, maintaining a hybrid role that combined research with clinical care. “At the same time, I continued clinical work for a couple of months each year, collaborating with Steve Rosenberg in the surgical branch.”

These early approaches were technically challenging and often unpredictable, but they laid the groundwork for later advances. “We started with basic approaches, moved to tumor-infiltrating lymphocytes, and eventually to engineered CAR T cells,” Parkinson said. “Progress has been steady, though often slower than those treating patients would like.”

If immunotherapy represented one trajectory, targeted therapy represented another—one that depended on a deeper understanding of cancer biology.

“When I joined Novartis in the late 1980s, we were among the first developing kinase inhibitors,” Parkinson said. At the time, the idea was controversial. “Early skepticism suggested kinase inhibitors wouldn’t work due to high intracellular ATP levels and structural challenges.”

But advances in molecular biology were beginning to change the landscape. The discovery of the Philadelphia chromosome and its associated oncogene created a clear therapeutic target. “The Philadelphia chromosome had been known since the 1960s, and by the 1980s the responsible gene was identified,” Parkinson explained.

The result was imatinib (Gleevec), a drug that would become a prototype for precision oncology. “Eventually, a small molecule inhibitor was developed that targeted it precisely.”

The clinical results were extraordinary. “By the third cohort in a Phase I trial, patients with chronic myelogenous leukemia showed dramatic responses—some within 24 hours,” Parkinson said. “It’s probably the only Phase I oncology trial where essentially every patient achieved remission.”

For Parkinson, the implications extended far beyond a single drug. “Of course, [Gleevec] was a unique case,” he said. “But it proved an important point: what once seemed impossible can become possible.”

Since then, the field has expanded dramatically. Hundreds of kinase inhibitors have been developed, with thousands more explored, reflecting a broader shift toward therapies grounded in specific molecular mechanisms.

Precision medicine—and its limits

As oncology evolved, so too did its language. “For years, we called it ‘personalized medicine,’” Parkinson said. “I used to joke that medicine has always been personalized—you’re always trying to determine what’s best for a specific patient in a specific context.”

He credits industry with popularizing a more precise term. “Although Pfizer popularized the term ‘precision medicine,’ I think it’s a better term,” he added, with a note of humor: “I have a few good Pfizer jokes—best shared over a drink.”

Yet the reality of precision medicine has proven more complex than its promise. “The evolution of therapeutics mirrored the models and biological understanding available,” Parkinson said. “Targeted therapies only emerged once we understood the biology. Diagnostics, however, lagged by about two decades.”

That lag remains a structural challenge. Parkinson founded a diagnostics company based on single-cell signaling technology developed at Stanford. “Technically, it worked—we solved major challenges in instrumentation, standardization, and analysis,” he said. “But we couldn’t establish a viable business model.”

The core issue was reimbursement. “Without adequate reimbursement from Medicare, even highly sophisticated diagnostics struggle commercially,” said Parkinson. “Better diagnostics can reduce the use of expensive drugs by identifying who won’t benefit—something that doesn’t always align with pharmaceutical business models.”

In recent years, Parkinson has focused increasingly on large-scale data integration, including his involvement with the GENIE consortium. The initiative aggregates genomic and clinical data across institutions, aiming to accelerate discovery and improve clinical decision-making. “GENIE has been a technical success,” he said. “But its long-term sustainability remains uncertain.”

The broader challenge, he argues, is conceptual as much as technical. “Looking forward, the field is evolving toward integrating multiple data types—genomics, transcriptomics, imaging, and more—to better understand tumor biology,” he said. “Sequencing alone isn’t enough. The challenge now is not a lack of data, but making sense of it—something where artificial intelligence will play an increasingly important role.”

Back to basics

Across academia, government, and industry—including roles at the NCI, Novartis, Amgen, and Biogen Idec—Parkinson sees a single throughline. “I remember an interview with a biotech company where an HR representative told me, ‘You seem to have done a lot of different things,’” he said. “I responded that I had really only done one thing: trying to improve cancer treatment, just from many different angles.”

Not every effort succeeded. “In one case, we developed a drug that performed beautifully in mice but failed in human trials,” he said. “That’s common in oncology—most ideas don’t translate. You don’t think of it as failure but as learning. Still, there’s a limit to how many ‘learnings’ one can appreciate.”

Reflecting on decades of progress, Parkinson emphasizes both how far the field has come and how much remains unresolved. “Outcomes have improved dramatically across several cancers, especially hematologic ones,” he said.

Yet he underscores a fundamental principle: that progress in cancer treatment comes down to understanding biology. “The better we understand it, the more effectively we can develop targeted therapies,” said Parkinson. “Without that understanding, we’re essentially guessing.”

At AACR 2026, Parkinson’s recognition underscores not just past achievements but a continuing trajectory—one shaped by the interplay of discovery, failure, and persistence. “Despite all the challenges,” he said, “[precision medicine] is still the most promising path forward.”


The post AACR 2026: David Parkinson and the Arc of Modern Cancer Therapy appeared first on Inside Precision Medicine.

10x Genomics Unveils Atera Spatial Platform at AACR Meeting

The genomics community’s long wait for 10x Genomics’ highly anticipated news is finally over. On Saturday night, at the Hard Rock Café Hotel in San Diego—across the street from the American Association for Cancer Research (AACR) conference—the company hosted the “Impossible” party to announce its new spatial instrument—the Atera.

Serge Saxonov, PhD, CEO of 10x Genomics, walking onto the stage to thunderous applause, noted that there is “a gap between what we need to see and what we have been able to measure.” The Atera, which enables whole-transcriptome spatial biology at scale, “obliterates the typical trade offs” that come with existing spatial tools, he said.

“This is the biggest launch in our history. I am the most excited I’ve ever been about any product, or any product category, across the board,” Saxonov told GEN. “It has been a long time in development, and it is what we have known the world needs for a long time. I think it will fundamentally change how we measure and understand biology, and it really puts research on a new trajectory. It is really exciting to be at a place now where we can deliver it to the world.”

Nuts and bolts

Atera offers more plex, throughput, and sensitivity than 10x Genomics’ Xenium—enabling whole-transcriptome at scale. More specifically, when compared to Xenium, Atera has four times the throughput, six times higher plex capacity for targeted assays, 3.6x higher plex, and 2–3x sensitivity for whole transcriptome assays.

10x Genomics Atera
10x Genomics Atera

The price for Atera is $495,000, and the instrument measures roughly 53” x 36” x 64” or (4.42 ft × 3 ft × 5.33 ft). Orders are currently being taken, and the instrument will be available in the second half of this year.

The instrument can run up to 800 1 cm2 whole transcriptome samples (FFPE and fresh frozen) per year, with flexible run configurations, and a greater than 5 cm² imageable area per slide (for greater than 2,000 mm² total tissue per run when using all four slides.)

There are 18,000-genes on the Atera WTA (whole transcriptome) with stackable customization of 1,000-gene Atera Select panels available now, and optional stacking of up to three 1,000-gene panels coming in the future.

“Spatial genomics with whole-transcriptome profiling capabilities is the ultimate approach to measure single cells in their tissue context,” Holger Heyn, PhD, ICREA professor at the Centro Nacional de Análisis Genómico (CNAG) and member of the Human Cell Atlas, added. “All other lower-plexity approaches have been just a warm-up phase leading to this application.”

Jasmine Plummer, PhD, associate member of the St. Jude Faculty and director of the Center for Spatial OMICs points out that the whole transcriptome, while exciting, can bring a big “sticker shock” for many researchers because it will require a lot more probes in contrast to a sequencing-based platform, where a library accesses all of the genes.

The instrument uses standard glass microscopy slides, which is exciting to Plummer. In the past, she said, slides have posed a challenge when coordinating with other researchers, and using regular slides will be more “pathology friendly.”

An end to tradeoffs? 

Existing spatial technologies, which are still relatively nascent in genomics, have been constrained by tradeoffs between plex, resolution, and throughput. Researchers have had to make choices and prioritize.

“In general, with the landscape as it is today, there is a tradeoff,” Nick Banovich, PhD, VP of scientific development at TGen, and professor of bioinnovation and genome sciences division and director of the Center for Spatial Multi-Omics (COSMO), told GEN. “The closer you walk toward whole transcriptome, the lower the per gene sensitivity.”

“The most exciting thing [about Atara],” he continued, “is that there is still quite good sensitivity with whole transcriptome breadth. That’s the huge advantage of this system; there is no tradeoff anymore.”

However, this launch comes just over three years after Xenium’s launch. Purchasing a new instrument so soon may pose a challenge. Plummer notes: “In this economy, with the uncertainty of scientific funding, it is concerning to ask customers—many of whom just landed a machine—to spend another several hundred thousand dollars.”

Why AACR?

Oncology is one of the most exciting, most promising applications of spatial, especially in the near term, noted Saxonov. This is, in large part, because the work exists across the spectrum—from basic discovery to translation to clinical applications. Spatial is unambiguously important, he asserted.

Unveiling at AACR “just made a lot of sense.”

In addition to the party, the company will host a digital launch event on Tuesday, April 21. Within the AACR program, a presentation from the German Cancer Research Center (DKFZ) will include data generated on the platform, highlighting Atera’s ability to uncover cancer biology not accessible with legacy approaches. Researchers distinguished multiple malignant and stem cell states across disease stages, within a single colorectal tumor sample, and mapped how these populations interact with the surrounding immune microenvironment. The data reveal a more complex immune landscape that could inform future therapeutic strategies and drug development. In addition, two posters (#7116, #6216) will include data from Atera.

The future

10x Genomics said that Atera will play a role in advancing large data studies. For example, the company noted that Atera will enable the goal of the Human Cell Atlas (HCA) as it continues its mission to map every cell type in the human body.

“With the Human Cell Atlas entering its next phase of generating spatially resolved atlases, whole-transcriptome approaches will be the workhorse for data generation,” Heyn told GEN.

“I am excited to see the Atara platform being launched now,” he added. “It is very timely as we ramp up production for the Human Cell Atlas 2.0 phase.”

Atera’s future

The company presented a roadmap with future plans at the AACR event, highlighting spatial proteomics, automation, base by base sequencing (a de novo sequencing assay) and software improvements.

Atera, Saxonov told GEN, is a fundamental platform that the company will continue enabling. It lays the groundwork for the next decade of research and work. This point in time, he said, feels similar to the early days of next generation sequencing (NGS). And although the company will continue to develop its other platforms and product lines, Atera has “massive amounts of headroom to keep building on top of it. It is the convergence of all these different technology stacks and different fields onto one.”

“What the platform can do right out of the gate is exciting. And all the things that it can do in the future will be really, really exciting,” he asserted.

The post 10x Genomics Unveils Atera Spatial Platform at AACR Meeting appeared first on GEN – Genetic Engineering and Biotechnology News.

The State of Multiomics & NGS

Broadcast Date: 

  • Time: 

Next-generation sequencing (NGS) has never been cheaper or more accessible. In turn, spatial biology, single-cell, and proteomics are fueling exciting advances in biology. The rapidly declining cost of whole-genome sequencing is empowering researchers to ask questions that were beyond reach just a few years ago. 

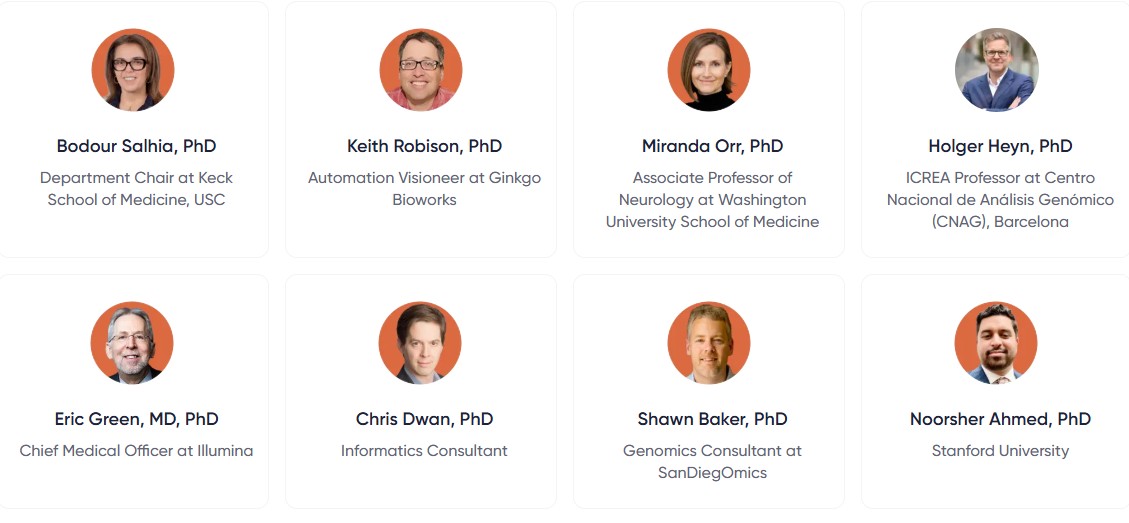
In The State of Multiomics & NGS virtual summit—sponsored exclusively by Illumina—GEN invites you to watch a superb line-up of presenters covering key topics in the world of multiomics, spatial biology, and NGS. This year’s summit features a broad selection of talks and panel discussions from renowned experts that offers our audience rich insights into the latest NGS platforms, spatial biology applications in neurodegenerative diseases and cell biology, and a critical look at data management challenges and solutions.

Among the highlights are:

  • A keynote presentation from Miranda Orr, PhD, on the use of spatial biology in studying Alzheimer’s and other neurodegenerative diseases
  • A deep dive into the latest NGS platforms and applications with veteran genomics analysts Keith Robison, PhD, and Shawn Baker, PhD
  • Modeling the proteome architecture of human cells with Noorsher Ahmed, PhD (Lundberg lab)
  • Chris Dwan on data management strategies for multiomics
  • And a sponsored breakout conversation featuring Illumina’s chief medical officer, Eric Green, MD, PhD, and cancer biologist Bodour Salhia, PhD (USC)

We look forward to seeing you on April 29. Registration is absolutely free! !

Guest Speakers Include

The State of Multiomics & NGS speakers

illumina logo

The post The State of Multiomics & NGS appeared first on GEN – Genetic Engineering and Biotechnology News.

TRACERx MRD Results Showcase ppmSeq’s Ultra-Sensitive ctDNA Detection at AACR

Minimal residual disease (MRD) continues to be a central focus at the AACR meeting. The small numbers of cancer cells that remain in the body after treatment helps gauge the effectiveness of a treatment and relapse risk. The ability to detect those cells, even in tiny amounts, is an ongoing goal of the cancer community.

At this year’s AACR, the sequencing company Ultima Genomics is announcing new findings in this area using its ppmSeq technology. The data will be presented across six abstracts, including a plenary session.

Highlighting the program will be initial TRACERx (TRAcking Cancer Evolution through therapy (Rx)) MRD data showcasing performance of ppmSeq relative to ultrasensitive bespoke panels.

TRACERx is a long-term study—one of the largest tumor evolution studies—funded by Cancer Research UK. The program analyzes how cancer evolves, spreads to other parts of the body, and develops resistance to treatments. Instead of taking just one biopsy, researchers sample different parts of the same tumor and metastases; the program involves sequencing multi-region and multi-time-point genetic data from over 3,200 tumor samples from over 800 lung cancer patients.

The data will be presented at a plenary session by Charles Swanton, FRCP, BSc, PhD,  professor at The Francis Crick Institute in the U.K. He will present an early validation pilot of ppmSeq across 50 plasma samples—using tumor-specific variants identified from prior whole genome sequencing—achieved high analytical sensitivity for ctDNA detection at low single-digit parts-per-million.

“TRACERx has always followed the science of cancer evolution wherever it leads,” said Swanton. “Improving the sensitivity of ctDNA detection is central to the wider ambition for MRD monitoring, and expanding studies across a broader patient population will give us the statistical power and clinical context to determine how whole genome MRD monitoring can be deployed at NHS scale and beyond.”

Data from collaborators will also be presented at the conference. Labcorp will present data from an independent analytical study of an assay developed in coordination with ppmSeq technology, including the performance across multiple solid tumor types in pre-surgical, treatment-naive plasma samples. This analysis of 120 non-cancerous donor samples showed specificity exceeding 99.9%, underscoring the ability of ppmSeq whole genome sequencing to accurately differentiate between cancerous and non-cancerous samples, minimizing false positives. Additional analysis across three commercially available cancer cell lines spanning 13 concentration levels from 0.5 to 500 parts per million showed a 95% limit of detection below 3 ppm, demonstrating the assay’s capacity to detect ultra-low levels of circulating tumor DNA (ctDNA).

“For a long time, the question has been whether you can get truly ultra-sensitive MRD detection from a whole genome approach without all the complexity of bespoke assays,” notes Gilad Almogy, PhD, CEO of Ultima Genomics. “What these AACR data show is that the answer is yes. We’re seeing ppmSeq deliver the level of sensitivity needed to make whole genome MRD practical, scalable, and much easier to deploy globally.”

The post TRACERx MRD Results Showcase ppmSeq’s Ultra-Sensitive ctDNA Detection at AACR appeared first on GEN – Genetic Engineering and Biotechnology News.

Brain Gene Variations Help Explain Neurological and Psychiatric Sex Differences

Thousands of genes are expressed differently in the brains of men and women, researchers have discovered.

The findings could help explain differences in neurodevelopmental, psychiatric, and neurodegenerative disorders between the sexes.

While men are more likely to experience schizophrenia, attention deficit hyperactivity disorder, and Parkinson’s disease, women are more prone to mood disorders and Alzheimer’s disease.

The U.S. study, in Science, is the first systemic single-cell survey of sex differences in gene expression across multiple regions of the human brain.

“Together, these findings provide a comprehensive map of molecular sex differences in the human brain and offer initial insight into their underlying mechanisms and potential functional consequences,” Alex DeCasien, PhD, from the National Institute of Mental Health in Bethesda, Maryland, told Inside Precision Medicine.

DeCasien and co-workers conducted a high-resolution analysis of gene expression in tissue samples from the brains of 15 men and 15 women using single-nucleus RNA sequencing.

They then used data from earlier large neuroimaging studies to select six cortical regions to sample, four of which showed sex-related differences in grey matter volume and two in which no such differences were found.

The team found subtle but widespread differences in gene activity between men and women. Biological sex explained very little of the variance in gene expression across the brain, at less than 1%, but differences were widespread—with more than 3000 genes showing different expression according to sex in at least one cortical region.

The greatest sex-related differences in gene expression were on the sex chromosomes. However, most of the genes showing sex-related variations in expression were autosomal—carried on one of the 22 numbered non-sex chromosomes.

The predominant driver for sex-biased expression of genes on these autosomal chromosomes were sex steroid hormones such as estrogen and testosterone.

Surprisingly, more than half the X chromosome genes in women were expressed in both alleles for at least one cell type. This indicated that many had escaped X chromosome inactivation—a female phenomenon in which one of the two X chromosomes is switched off early in development to stop women producing double the number of X-linked gene products to men.

“That finding has implications for understanding sex-biased disease susceptibility because several genes implicated in neurodevelopmental disorders reside on the X chromosome,” commented Jessica Tollkuhn, PhD, from Cold Spring Harbor Laboratory, and S Marc Breedlove, from Michigan State University, in an accompanying Perspective article.

They noted that autosomal genes showing sex-biased expression were substantially enriched for extracellular matrix components, hormone signaling pathways, and metabolic processes. “Genes with greater expression in women were enriched for mitochondrial and synaptic functions, whereas male-biased genes were associated with metabolic and structural pathways,” the editorialists added.

“By pinpointing these sexually differentiated processes, the data provide a treasure trove for the discovery of biomarkers of and/or therapeutic targets for differential disease risk in men and women.”

DeCasien and team added: “These findings raise the possibility that sex differences in gene expression modulate the magnitude of genetic effects at risk loci, contributing to differences in disease vulnerability and to reduced portability of polygenic risk prediction across sexes.”

The post Brain Gene Variations Help Explain Neurological and Psychiatric Sex Differences appeared first on Inside Precision Medicine.

Integrated Sample Preparation System Standardizes and Streamlines Pre-Analytical Workflows

Invivoscribe launched the PrepQuant™ sample preparation platform that integrates nucleic acid extraction, concentration, and quantification with a single automated instrument. The product is designed to standardize sample preparation and simplify pre-analytical workflows to reduce costs and eliminate a primary source of inconsistency in molecular testing.

Developed in collaboration with Hitachi High-Tech Corporation, PrepQuant combines Invivoscribe’s experience in developing standardized molecular assays, providing global clinical testing services, along with Hitachi High-Tech’s technological and manufacturing capabilities

The PrepQuant system is assay agnostic, generating highly concentrated genomic DNA and cell free DNA (cfDNA) yields for next-generation sequencing (NGS), qPCR, and digital PCR (dPCR) assays. By consolidating multiple steps in a single platform, the system can lab operating costs, sample variability, and lab bench space, while optimizing tests results.

“PrepQuant represents a significant advancement in our commitment to standardize the entire testing process, starting with the pre-analytical workflow,” said Jeff Miller, CEO and CSO of Invivoscribe. “This is particularly important in the era of precision medicine, where reliability of measurable residual disease and liquid biopsy results depend markedly on the quality and consistency of the starting material.”

“The concept for the [product] was driven directly by insights from LabPMM, our global network of testing laboratories,” added Jordan Thornes, vice president, global clinical lab operations. “Our teams recognized the limitations of currently available automated instruments, particularly the labor-intensive nature and increased risk of errors associated with running three separate protocols across multiple instruments. This all-in-one system was designed to reduce costs, while addressing those challenges and significantly improving operational efficiency.”

The PrepQuant is designed and validated for use with blood, plasma, and bone marrow specimens, with ongoing development for additional specimen types. Invivoscribe will officially unveil the product at the American Association for Cancer Research (AACR) Annual Meeting in San Diego, at booth #3459 from April 19–22.


The post Integrated Sample Preparation System Standardizes and Streamlines Pre-Analytical Workflows appeared first on GEN – Genetic Engineering and Biotechnology News.

An inducible base editing platform for cancer functional genomics in vivo

Nature Biotechnology, Published online: 15 April 2026; doi:10.1038/s41587-026-03079-3

We developed a functional genomics platform using a small-molecule-controllable base editor that enables gene editing with reduced cellular toxicity and minimal transcriptional perturbation. The resulting high efficiency of the method potentiates in vivo inducible genetic screening, allowing systematic identification of critical residues in cancer therapeutic targets.

Can psychiatric genetics advance without incorporating a lifecourse perspective?

Psychiatric disorders unfold over the lifecourse, yet genomic studies of these conditions overwhelmingly rely on phenotypes collected at a single time point, often in adulthood. Genome-wide association studies (GWAS) of psychiatric conditions may therefore miss genetic variants with time-varied relevance to etiology, prevention and treatment, such as those that influence trajectories of symptoms and behaviors, age-at-onset, course of treatment response, and co-evolution of comorbidities. With recent advances in longitudinal biobanks and analytic tools, we posit that incorporating a lifecourse perspective in psychiatric genetics will enable critically relevant insights into each of these areas of investigation.

Pregnancy Sickness Study Identifies New Genetic Links

The University of Southern California (USC) research team that identified the hormone-encoding gene GDF15 as a key driver of pregnancy sickness has identified nine additional genes linked to its most severe form, hyperemesis gravidarum (HG). Six of the identified genes had not been previously linked to the condition.

The Keck School of Medicine of USC team and international collaborators conducted a genome-wide association study (GWAS), scanning the entire genome for differences between women who developed HG during pregnancy and those who did not. They analyzed data from more than 10,000 women with the condition and more than 450,000 controls across European, Asian, African, and Latino ancestries. Their findings offer new clues about the condition and new hope for those affected.

Marlena Fejzo, PhD, a clinical assistant professor of population and public health sciences in the Center for Genetic Epidemiology at the Keck School of Medicine, led the present study and earlier research linking GDF15 to HG. Fejzo told GEN, “The study is much larger than previous studies and on a more diverse population allowing for identification of new genes associated with HG … The new genes give us new directions to explore for prediction, diagnosis, treatment, and response to therapies.”

Fejzo is first author of the team’s published report in Nature Genetics (“Multi-ancestry genome-wide association study of severe pregnancy nausea and vomiting”), in which the team stated, “Potential roles for candidate genes in appetite, insulin signaling, and brain plasticity provide pathways to explore etiological mechanisms and therapeutic avenues.”

HG, which affects about 2% of women, causes nausea and vomiting so severe that eating can become extremely difficult. “Most pregnancies are affected by nausea and vomiting (NVP), but in 0.3–10.8% of pregnancies the symptoms can be severe enough to cause maternal weight loss and adverse maternal and fetal outcomes,” the authors wrote. HG in its most severe form can even be life threatening.

HG was long misunderstood and often dismissed as psychological, growing evidence shows that it has a strong biological and genetic basis and can lead to severe malnourishment, putting both mother and baby at risk. Current treatments for HG are frequently ineffective in improving patient symptoms, the authors further pointed out, and so increase the risk of pregnancy termination, postpartum depression, and suicidal ideation, along with other maternal and offspring comorbidities. “Therefore, understanding of HG etiology is critical to begin to address the negative impact severe NVP has on maternal and child health.”

While historical hypotheses have previously centered around human chorionic gonadotropin (hCG), recent large-scale genetic studies have implicated the GDF15 gene encoding growth differentiation factor-15—a hormone associated with nausea and vomiting, the authors further pointed out. Earlier research by Fejzo and an international team had shown that the link between HG and GDF15 lies in women’s sensitivity to the hormone. They found that women exposed to lower levels of the hormone before pregnancy because of a mutation in the gene experience more severe symptoms, while women exposed to higher levels of the hormone before pregnancy have less severe nausea and vomiting symptoms.

“GDF15 was identified as the greatest genetic risk factor for HG in both a genome-wide and an exome-wide association study, and a rare mutation in GDF15 was associated with a greater than tenfold increased risk for HG,” the scientists noted in their newly reported study. Fejzo explained to GEN, “The mutation in GDF15 is rare. People who carry the mutation have abnormally low levels of GDF15 when they are not pregnant and that increases their risk of being hypersensitive to it during pregnancy when it is produced in massive amounts by the placenta.”

Commenting on their prior work implicating a role for GDF15 and HG, Fejzo further explained to GEN, “In our first GWAS study we found the association between the GDF15 gene and HG. Next, we published a whole-exome sequencing study that identified a mutation in GDF15 associated with HG. Then we published our study in Nature which provided strong evidence that hypersensitivity to the rise of GDF15 in pregnancy (due to low pre-pregnancy GDF15 in circulation) is the main driver of the condition.”

For their newly reported study the researchers carried out a multi-ancestry genome-wide association study of 10,974 HG/excessive vomiting in pregnancy cases and 461,461 controls across European, Asian, African, and Latino ancestries from nine contributing studies.

The results identified 10 genes that were linked to HG, including four that had previously been identified, and six new genes. “Because this is the largest study of HG ever conducted, we’ve been able to tease out important new details that were previously unknown,” said Fejzo. “The fact that we’ve studied women from multiple ancestry groups suggests that these results may be generalizable across a broad population.”

The four genes previously identified were growth differentiation factor 15 (GDF15), GFRAL, which produces the receptor for the GDF15 hormone of the same name, and IGFBP7 and PGR, both of which are involved in development of the placenta. The strongest link by far was to GDF15, which rises sharply during pregnancy. “We know that GDF15 and it’s receptor GFRAL are the main drivers and are in a signaling pathway that causes aversions, nausea, and vomiting,” Fejzo told GEN. “More work needs to be done to explore the other associations, but since studies suggest manipulating progesterone and/or IGFBP7 may not be safe in pregnancy, current studies are focusing on the GDF15 pathway.”

The six newly identified genes offer further clues that might help explain the basis of HG or point to new ways of treating it. They include FSHB, TCFL72 SLITRK1, SYN3, IGSF11, and CDH9. “Now that we’ve more than doubled the genes associated with HG, we can dig deeper into the biology behind this condition, as well as new possible pathways for treating it,” Fejzo said. Speaking to GEN, the researchers noted, “Because the new associations are novel, we need to understand the roles they may play in normal pregnancy and then compare that to pregnancies affected by HG.”

Of the newly identified genes, TCF7L2 stands out because it is one of the strongest genetic risk factors for type 2 diabetes and is also associated with gestational diabetes. “This is a brand-new target, and it’s not yet clear what it’s doing in pregnancy,” Fejzo said. In further commentary to GEN, Fejzo added, “The TCF7L2 gene is a type 2 diabetes-associated gene and a transcription factor that may control glucagon-like peptide-1 (GLP-1) expression and has been associated with liraglutide effects resulting in greater weight loss in obesity. So understanding its role in that rapidly evolving therapeutic arena has potential.”

Several of the other genes identified are involved in appetite and nausea, as well as brain plasticity, or how the brain learns and adapts to new information. Fejzo suggests the brain may learn to associate certain foods with feeling sick, leading to strong, lasting aversions during pregnancy. More research is needed to explore this possibility. “Other genes are associated with learning flexibility so we hypothesize that they may play a role in conditioned taste aversion and may provide new targets to alter or dampen learned aversions,” Fejzo told GEN. Historically, people believed the pregnancy hormone hCG was the cause, but we found no evidence to support that and instead, fascinatingly, we found a link to the follicle stimulating hormone receptor.”

Of the ten candidate genes six—GDF15, GFRAL, IGFBP7, PGR, TCF7L2 and SYN3—have been linked with cachexia—a wasting condition with similar symptoms to HG, including loss of appetite, weight loss and muscle wasting, the scientists noted. “Manipulation of GDF15, GFRAL, IGFBP7, PGR and TCF7L2 in animal models has shown effectiveness in reducing symptoms of cachexia. Thus, assuming analogous functions for these factors in HG, there is both genetic and biological support for causal and potentially reversible contributions for these genes in NVP.”

The researchers also found that some genes linked to HG were associated with other pregnancy outcomes. “This study also identified individual associations between risk genes and adverse outcomes including shorter pregnancy duration, pre-eclampsia, and birth weight,” they noted.

Several medications are available for treating HG, but even the most effective, Zofran, only partly relieves symptoms for about half of patients. The new findings reveal new potential treatment targets and could possibly also help match existing medications to patients based on their genetic profiles. “The ten genetic associations provide intriguing avenues to advance our understanding and pursue therapeutic pathways for a common pregnancy condition that in its most severe form is associated with substantial morbidity and even mortality for mothers and exposed offspring,” the scientists concluded.

Fejzo and her team just received approval to launch a clinical trial of metformin, a widely used diabetes medicine that increases GDF15 levels. The study will test whether taking metformin before pregnancy can desensitize women to the hormone, potentially reducing nausea and vomiting or preventing HG in women who have had it before. GEN was told, “We will be initiating a clinical trial to increase GDF15 prior to pregnancy in patients with a history of HG and planning to conceive to desensitize them to the hormone’s rapid rise in early pregnancy. We and others have shown preliminary evidence that this approach may work as in our retrospective study pre-pregnancy metformin use was associated with a significant reduction in HG risk.”

The post Pregnancy Sickness Study Identifies New Genetic Links appeared first on GEN – Genetic Engineering and Biotechnology News.