

<![CDATA[New report reveals private practice delivers 113.6M mental health sessions, yet business training gaps and access mismatches persist.]]>
<![CDATA[A new report shows private practice clinicians deliver over 113 million sessions of mental health care, making up the majority of outpatient care.]]>
iCARE Self-Guided Digital Intervention for Postpartum Depression in Danish Mothers: Formative Research Using User-Centered Design
<strong>Background:</strong> Postpartum depression (PPD) is a major public health concern. Despite advancements in treatment, many barriers to accessing care remain. There has been a growing interest in digital interventions for the prevention and treatment of PPD. However, for mothers with mild and moderate symptoms of depression, there is a limited offer of self-guided internet-based interventions developed with user input and with considerations on how to integrate the intervention into stepped care models for PPD. <strong>Objective:</strong> The aim of this study was (1) to describe the process of the design and development of iCARE, a self-guided digital psychological intervention for mothers with mild and moderate symptoms of PPD in Denmark, (2) present the program’s theory illustrated by a logic model, and (3) explore its initial usability and prospective acceptability. <strong>Methods:</strong> Applying user-centered design methods, the intervention development followed six steps: (1) a literature review to identify evidence‑based therapeutic components of self‑guided interventions for PPD, (2) interviews with women with lived experience of PPD and group discussions with mental health experts and home‑visiting providers to identify user needs, (3) iterative design and content development with stakeholder feedback in collaboration with the Department of Digital Psychiatry, (4) prototype testing using think‑aloud usability sessions and interviews with 5 mothers, (5) a group cognitive walkthrough with mental health experts, and (6) final refinement and implementation of the iCARE program with developers and designers. <strong>Results:</strong> Initial interviews with mothers and maternal health care providers emphasized the importance of a digital intervention offering timely psychoeducation, coping strategies, and pathways to in-person care while addressing the diversity of expressions of PPD symptoms. Stakeholders recommended a flexible program, multimodal content, and integration into maternal care systems with community health nurses supporting engagement and participation. The prototype was designed to be user-centered, engaging, and with multiple interactive features. It included components on psychoeducation, cognitive exercises grounded in cognitive behavioral therapy, acceptance and commitment principles, and mood-monitoring. The prototype was designed to be user-centered and engaging, with interactive features and components on psychoeducation, cognitive exercises grounded in cognitive behavioral and acceptance and commitment principles, and mood-monitoring. Prototype testing indicated high prospective acceptability and led to refinements across 6 themes: appropriateness of content; motivation and engagement; inclusivity and gender representation; clarity of instructions and data use; understanding of therapeutic method; and usability, layout, and navigation. <strong>Conclusions:</strong> iCARE is a self-guided internet-based psychological intervention for mothers with mild and moderate symptoms of PPD in Denmark. It was developed with user input by using qualitative methods, user-centered design, and psychological theory. Further research is needed to evaluate the feasibility and effectiveness of the program in a randomized controlled trial and its integration into maternal health care models such as universal PPD screening and home-visiting.

Early Detection of Alzheimer’s Disease and Related Dementias From Spontaneous Speech Using Foundation Speech and Language Models: Comparative Evaluation
<strong>Background:</strong> Alzheimer’s disease and related dementias (ADRD) are progressive neurodegenerative conditions where early detection is critical for timely intervention and care planning. However, current diagnostic methods are often inaccessible, costly, and delayed, especially for underserved populations. There is a growing need for scalable, noninvasive tools that can support timely diagnosis. Spontaneous speech contains rich acoustic and linguistic markers that can serve as noninvasive behavioral markers for cognitive decline. Foundation models, pretrained on large-scale audio or text data, generate high-dimensional embeddings that encode rich contextual and acoustic information. <strong>Objective:</strong> This study benchmarks open-source foundation language and speech models to evaluate their effectiveness in detecting ADRD from spontaneous speech as a potential solution for early, noninvasive, and scalable ADRD detection. <strong>Methods:</strong> In this study, we used the Pioneering Research for Early Prediction of Alzheimer’s and Related Dementias EUREKA (PREPARE) Challenge dataset, which consists of audio recordings from over 1600 participants with 3 distinct categories of cognitive decline: healthy control (HC), mild cognitive impairment (MCI), and Alzheimer’s disease (AD). We further excluded samples that are non-English, nonspontaneous speech, or of poor quality. Our final samples included 703 (59.13%) HC, 81 (6.81%) MCI, and 405 (34.06%) AD cases. We systematically benchmarked 18 open-source foundation speech and language models to classify cognitive status into 3 categories (HC, MCI, or AD). Post hoc interpretability analysis was performed for the best-performing model using Shapley additive explanations linking high-dimensional embeddings with explainable acoustic and linguistic markers. <strong>Results:</strong> Whisper-medium model achieved the highest performance among speech models at 0.731 accuracy and 0.802 area under the curve, while Bidirectional Encoder Representations from Transformers with pause annotation achieved the top accuracy of 0.662 and 0.744 area under the curve among language models. Overall, ADRD detection based on state-of-the-art automatic speech recognition model-generated audio-embeddings outperformed other models, and the inclusion of nonsemantic information, such as pause patterns, consistently improved the classification performance of text-embedding–based models. <strong>Conclusions:</strong> Our work presents a comprehensive comparative evaluation of state-of-the-art speech and language models for AD and MCI detection on a large, clinically relevant dataset. Embeddings derived from acoustic models, which capture both semantic and acoustic information, show promising performance and highlight the potential for developing a more scalable, noninvasive, and cost-effective early detection tool for ADRD.

Direct modulation of human GABA-A α1β2γ2 receptors by the endocannabinoid 2-arachidonoylglycerol: implications for cannabinoid-related ligands and limitations for anxiolytic drug development
Anxiety disorders are associated with impaired inhibitory neurotransmission mediated by γ-aminobutyric acid type A (GABA-A) receptors. Although benzodiazepines remain effective anxiolytics, their clinical utility is limited by sedation, cognitive impairment, tolerance, and dependence, prompting the search for mechanistically distinct GABAergic modulators. Among cannabinoid-related molecules, the strongest evidence for direct GABA-A receptor modulation concerns the endocannabinoid 2-arachidonoylglycerol (2-AG), which potentiates recombinant human α1β2γ2 receptors through residues located in the M4 helix of the β2 subunit. Here, we review the structural architecture, biophysical properties, and pharmacological profile of the human GABA-A α1β2γ2 isoform as the relevant molecular framework for evaluating this mechanism, while discussing the broader relevance of cannabinoid-related ligands and selected phytocannabinoids without assuming mechanistic equivalence. We further assess the hypothesis that 2-AG reaches the β2-M4 site through a membrane-access route and identify five conceptual barriers that currently limit translation of this mechanism into anxiolytic drug development: supraphysiological effective concentrations, unresolved synaptic-versus-extrasynaptic actions, uncertain subtype selectivity, incomplete validation of lipid-environment effects, and lack of clinical evidence linking this mechanism to anxiolysis in humans. We conclude that direct modulation through β2-M4 defines a mechanistically intriguing allosteric pathway distinct from benzodiazepine action; however, its location on a shared β2 subunit and the micromolar concentrations required for modulation represent substantial obstacles to the rational design of anxioselective agents based on this mechanism.
Internalizing and externalizing pathways to internet gaming disorder: the roles of anger and social anxiety
BackgroundInternet Gaming Disorder (IGD) represents a significant behavioral health concern, yet the roles of internalizing and externalizing psychological vulnerabilities in its development remain underexplored, particularly in Arabic-speaking populations.ObjectiveThis study examined anger and social anxiety as distinct externalizing and internalizing predictors of IGD severity in a Saudi Arabian community sample.MethodsA cross-sectional survey was administered to 303 participants (60.1% female; estimated mean age = 29.79 years, SD = 8.83) across five regions of Saudi Arabia. Participants completed the Internet Gaming Disorder Scale–Short Form (IGDS9-SF), a three-item Anger Screening Scale, and a two-item Social Anxiety screener. Hierarchical linear regression and structural equation modeling (SEM) were conducted to examine unique and incremental contributions of anger and social anxiety to IGD symptoms.ResultsAnger and social anxiety were strongly intercorrelated (r = .86, p <.001) but demonstrated divergent patterns in multivariate models. Hierarchical regression indicated that both predictors contributed unique variance when entered simultaneously, with anger positively and social anxiety negatively predicting IGD after controlling for shared variance. However, SEM clarified that only social anxiety significantly predicted latent IGD severity (β = .32, p = .027), whereas anger did not (β = .07, p = .68). The final model explained approximately 13% of variance in IGD symptoms.ConclusionsSocial anxiety was associated with IGD severity as a distinct internalizing correlate, consistent with avoidance-based coping and online social preference accounts. These preliminary, cross-sectional findings suggest that social anxiety warrants consideration in future IGD screening and research efforts in Arabic-speaking contexts.
Understanding and Targeting Self-Regulatory Control in Bulimia Nervosa
Conditions: Bulimia Nervosa; Feeding and Eating Disorders; Mental Disorders
Interventions: Other: Real fNIRS Neurofeedback; Other: Sham-Control fNIRS Neurofeedback; Other: SmartPhone Intervention
Sponsors: Icahn School of Medicine at Mount Sinai
Not yet recruiting
Interventions: Other: Real fNIRS Neurofeedback; Other: Sham-Control fNIRS Neurofeedback; Other: SmartPhone Intervention
Sponsors: Icahn School of Medicine at Mount Sinai
Not yet recruiting
Alexa Grasso on Mental Health Fitness
Alexa Grasso shares her routine for staying mentally strong in and out of the Octagon
In recognition of Mental Health Awareness Month, the Child Mind Institute has launched the Mental Health Fitness campaign — a national call to action highlighting the importance that caring for one’s mental health is just as important as physical health.
Alexa Grasso knows the importance of prioritizing her mental well-being alongside her physical training. She uses breathwork to stay grounded, acknowledges emotions instead of suppressing them, and practices mindfulness — highlighting that true strength comes from training the mind with the same discipline as the body.
“What I do when I feel stressed or overwhelmed by life, is breathing. It’s super important to breathe, to think clearly and give time to each emotion. To live it.”
About Anna Sitar
Alexa Grasso is a Mexican mixed martial artist and one of the top competitors in women’s flyweight diving of the UFC. Known for her sharp boxing and calm presence in the Octagon, she made history in 2023 by becoming the first Mexican-born woman to win a UFC championship. Grasso’s rise through the sport has been marked by discipline and resilience, earning her recognition as a trailblazer for Mexican athletes in MMA.
About Mental Health Fitness
For decades, we’ve understood that physical fitness doesn’t just happen — it takes skills, regular practice, and a supportive environment. The same is true for mental health. Developed by experts at the Child Mind Institute for three different age groups, our Mental Health Fitness guides have been used by more than 1.8 million students, caregivers, and educators to build emotion regulation skills and resilience. Whether your child is 5 or 15, struggling or thriving, they can learn these skills. And you can practice alongside them. Learn more at Mental Health Fitness.
Related Resources
- How to Help Children Calm Down
- What Is Co-Regulation?
- How to Model Healthy Coping Skills
- Raising Confident, Independent Children
The post Alexa Grasso on Mental Health Fitness appeared first on Child Mind Institute.
The Child Mind Institute Hosts 2026 Spring Luncheon “Future-Proofing Your Kids: Empowered Parenting in the Digital Age”
New York Times bestselling author Lisa Damour, PhD, led a thoughtful discussion to honor Mental Health Awareness Month
New York, NY – The Child Mind Institute, the leading independent nonprofit dedicated to transforming the lives of children struggling with mental health and learning disorders, hosted its 2026 Spring Luncheon on Monday, May 11. The event featured a dynamic discussion between Lisa Damour, PhD, a three-time New York Times bestselling author and host of the podcast, Ask Lisa: The Psychology of Raising Tweens & Teens, and Dave Anderson, PhD, Vice President of Public Engagement and Education and a senior psychologist at the Child Mind Institute. Their conversation was moderated by Ali Wentworth, an actress, comedian, author, and host of the television show, The Parent Test.
The event brought together advocates and distinguished individuals dedicated to equipping children and families with the skills they need to thrive in today’s rapidly evolving online and social environments. Attendees included Carson and Siri Daly, Jeannie Gaffigan, Kyle MacLachlan, Zibby Owens, and Alysia Reiner.
“We are raising children in a world fundamentally different from any generation before them…a world where childhood unfolds not just in homes and schools but online,” said Harold S. Koplewicz, MD, founding president and medical director of the Child Mind Institute. “Technology brings creativity and connection but also real risks: constant comparison, disrupted sleep, compulsive engagement, and exposure to harmful content. Our job is to help kids build the skills to navigate this world with resilience, confidence, and balance.”
The discussion centered on kids and families and how they can build healthy habits and resilience as they face the demands and distractions of a world increasingly reliant upon and centered around digital technology.
“My umbrella concern is what the conversation about technology is doing to the relationship between adults and kids. The single most powerful force for youth mental health is strong relationships with caring adults,” said Dr. Damour.
“If we focus on driving causal factors — such as family relationships, academic success, in-person friendships, sleep, and movement — we end up promoting a child’s wellness far more than by taking technology away,” said Dr. Anderson.
The luncheon raised over $260,000 to support the Child Mind Institute’s mission to change the lives of children with mental health and learning disorders in the United States and around the world.
The luncheon was co-chaired by Chris Mack, Lisa and Guy Metcalfe, Zibby Owens, and Jil Schaps. The host committee included Robyn and Paul Goldschmid, Desiree Gruber, Molly Jong-Fast, Breanna and John Khoury, Isabelle Krishana, Arielle Tepper, and Sarah J. Wetenhall.
Photos from the luncheon can be found here.
This special event is part of the Child Mind Institute’s programming during Mental Health Awareness Month. The Child Mind Institute recently launched its latest campaign, Mental Health Fitness. Physical fitness doesn’t just happen — it takes skills, regular practice, and a supportive environment. The same is true for mental health. Alongside relatable content from influencers and world-renowned athletes, the Mental Health Fitness resources from the Child Mind Institute provide kids and families with five core mental health skills they can practice every day.
About the Child Mind Institute
The Child Mind Institute is dedicated to transforming the lives of children and families struggling with mental health and learning disorders by giving them the help they need. We’ve become the leading independent nonprofit in children’s mental health by providing gold-standard, evidence-based care, delivering educational resources to millions of families each year, training educators in underserved communities, and developing tomorrow’s breakthrough treatments.
Visit Child Mind Institute on social media: Instagram, Facebook, X, LinkedIn
For press questions, contact our press team at childmindinstitute@ssmandl.com or our media officer at mediaoffice@childmind.org.
The post The Child Mind Institute Hosts 2026 Spring Luncheon “Future-Proofing Your Kids: Empowered Parenting in the Digital Age” appeared first on Child Mind Institute.
Finding Answers When Your Child Is Struggling: Introducing Ask Kai
Every day, parents reach out to the Child Mind Institute with questions that keep them up at night: Why does my daughter have such strong emotions? Why can’t my son sit still in class? Is this normal anxiety or something more?.
These questions are urgent, but finding answers isn’t easy. The wait time to see a children’s mental health professional can be months or even years. Many families don’t know where to start, what’s normal for their child’s age, or whether their concerns warrant professional help. And with nearly 1 in 5 children experiencing a mental health challenge within the U.S. alone, too many families are navigating this uncertainty on their own.
That’s why we built Ask Kai — a free, evidence-based symptom checker designed specifically for children’s mental health, available in both English and Spanish.
Meet Ask Kai
Ask Kai is a conversational symptom checker that helps parents and caregivers understand their child’s behavior and points them to appropriate resources. Through a streamlined series of questions and prompts, Ask Kai gathers information about your child’s challenges and provides personalized recommendations in minutes.
Ask Kai doesn’t diagnose your child. Instead, it helps you:
- Understand whether your concerns align with common mental health challenges
- Learn what to look for and what questions to ask
- Find evidence-based resources specific to your child’s needs
- Know how to find additional support if needed
Think of Ask Kai as a knowledgeable guide who helps you make sense of what you’re seeing and points you toward your next best step.
How Ask Kai works
If you’ve ever used a symptom checker for physical health, you know the challenge: enter “headache,” and you might walk away convinced you have everything from a sinus infection to a brain tumor. Mental health symptom checkers face even greater challenges. Because every child is different, what looks like defiance in one child could look like anxiety in another, and a behavior that’s appropriate at age five might be cause for concern at age ten. On top of that, mental health conditions often overlap.
So how did we build a tool that captures this complexity without overwhelming families? We focused on expertise and evidence:
- Clinicians and data lead the way: Ask Kai was built using thousands of child mental health evaluations — open datasets spanning different ages, backgrounds, and conditions — and developed in close collaboration with child psychologists and psychiatrists.
- Evidence-based question selection: Rather than asking hundreds of questions, we used machine learning to identify which combinations of questions provide the most meaningful information without burdening families.
- Comprehensive resource library: Every recommendation Ask Kai makes is matched to our extensive collection of guides, articles, expert perspectives, and pathways to professional help.
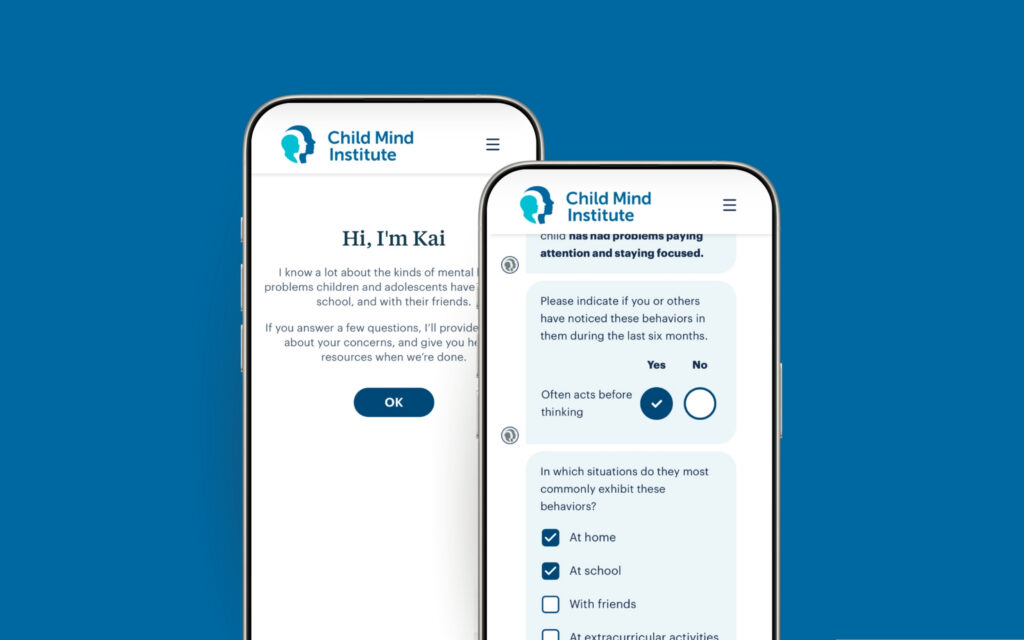
Here’s what happens when you use Ask Kai
Step 1: Initial Screening
You’ll answer a brief set of questions about your child’s behavior, emotions, and how these challenges affect daily life. You’ll also have the chance to describe in your own words what brought you to Ask Kai. These questions cover the areas where we see the most common concerns.
Step 2: Personalized Deep Dive
Based on your responses, Ask Kai selects targeted follow-up questions that dig deeper into the areas you flagged, whether that’s attention and focus, social anxiety, learning, or other behavioral challenges.
Step 3: Matching You to Resources
Ask Kai analyzes your complete response pattern, including the severity and impact of the behaviors you described, and provides a report with recommendations relevant to your child’s age, challenges, and needs.
What Ask Kai can assess
We designed Ask Kai to explore the areas where we can provide the most help to the most families. Ask Kai offers comprehensive screening and resources for:
Attention-deficit/hyperactivity disorder (ADHD) is a neurodevelopmental disorder that is characterized by difficulties with attention, organization, and impulsive behaviors. Symptoms are usually divided into inattentive behaviors or hyperactive and impulsive behaviors. Inattentive symptoms may include making careless mistakes, being easily distracted, difficulty listening to instructions, trouble with organization, and forgetfulness. Hyperactive/impulsive symptoms may include fidgeting or squirming, trouble playing quietly, extreme impatience, as well as constant talking and interrupting.
Autism spectrum disorder (ASD) is a neurodevelopmental disorder that begins in utero, but children may not get diagnosed until they’re in preschool or even older, when symptoms become more apparent. The disorder is characterized by deficits in social communication skills as well as restrictive or repetitive behaviors. Symptoms include a wide range of impaired cognitive abilities, language skills, and behaviors. These symptoms have been thought of as a set of disorders but are now being considered one disorder that presents along a spectrum.
Depression is a mood disorder that can cause children and teenagers to feel very sad and hopeless. Kids with depression have trouble enjoying things they used to love. They may also seem listless and easily annoyed.
Generalized anxiety disorder is characterized by excessive, persistent, and unreasonable worries about everyday things, like doing well in school or sports. In general, kids with this disorder worry a lot about being perfect.
Oppositional defiance disorder is a disruptive behavior disorder characterized by ongoing persistent, age-inappropriate disobedience and resistance to authority. To be diagnosed with this disorder, children would have had to display extreme behavior issues for at least six months. Diagnosis occurs around early elementary school ages and stops around adolescence.
Social anxiety disorder is a type of anxiety characterized by such intense self-consciousness and fear of embarrassment in social situations that the individual avoids social events; also known as social phobia. While some kids with this disorder are specifically afraid of performance engagements like public speaking or sporting events, others are scared of general social situations.
Specific phobia is an anxiety disorder characterized by an excessive and irrational fear of an object, situation, or place. Common specific phobias include dogs, clowns, bugs, the dark, and loud noises.
For young children, bathroom troubles are often a normal part of growing up. But once kids pass potty-training age, peeing or pooping in places other than the toilet might be a sign of an underlying issue. If it involves urine, it’s called “enuresis.” If it involves feces, it’s called “encopresis.”
Nonverbal learning disorder (NVLD) is a condition characterized by difficulty processing visual-spatial information — which involves the brain’s ability to interpret and respond to visual input, including where things are in space. These skills are used to do things like putting together a puzzle or reading a diagram.
Specific learning disorder is a condition that causes children to have difficulty with reading, writing, and/or math. If they have trouble with reading, the disorder is called dyslexia. If they have trouble with writing, it’s called dysgraphia. If they have trouble with math, it’s called dyscalculia. Symptoms are typically first noticed when the child is in preschool or early elementary school.
These ten areas represent some of the most common mental health concerns in childhood. They’re also areas where we have robust data, validated assessments, and comprehensive resources.
What if your concerns aren’t on this list?
Ask Kai can still help. When you describe your situation in your own words, Ask Kai analyzes your response to identify additional concerns and match you to appropriate resources. Your child’s challenges don’t need to fit neatly into one of these categories for Ask Kai to provide value.
However, we will only make recommendations when we’re confident in the evidence behind them. If a particular concern isn’t well represented in our data, we won’t try to provide guidance in that area. Regardless of the results, everyone receives a core set of resources that we believe are helpful for all families navigating children’s mental health.
Your privacy matters
We take data privacy seriously:
- Your responses are confidential and secure
- Free-text responses are analyzed using secure AI systems
- We don’t share your individual information with third parties
- In addition to providing you with resources, your data will only be used to improve Ask Kai
Try Ask Kai Today
If you’re wondering whether your child’s behavior is typical or cause for concern, Ask Kai can help. In just 10 to 15 minutes, you’ll get personalized insights and resources to guide your next steps.
You don’t have to figure this out alone. We’re here to help.
If your child is in crisis, expressing thoughts of self-harm, experiencing severe symptoms, or in immediate danger, please seek emergency help right away. Call 988 (Suicide and Crisis Lifeline), text “HELLO” to 741741 (Crisis Text Line), or go to your nearest emergency room.
Frequently Asked Questions
How long does it take?
Most families complete Ask Kai in 10–15 minutes.
Who should use this tool?
Parents, caregivers, and professionals working with children ages 4–18.
Will I get a diagnosis?
No. Ask Kai provides screening information and resources, but only a qualified clinician can provide a diagnosis.
What if I need immediate help?
If your child is in crisis, please call 988, text “HELLO” to 741741, or visit your nearest emergency room.
What makes this different from other symptom checkers?
Ask Kai was built specifically for children’s mental health, uses evidence-based assessments, provides personalized follow-up questions, and was developed in close collaboration with child mental health professionals.
The post Finding Answers When Your Child Is Struggling: Introducing Ask Kai appeared first on Child Mind Institute.