California may be known as the Golden State, but it may well be referred to as the Genome Editing state after this week’s announcement of an inter-state partnership. The University of California (UC), San Diego, and the Innovative Genomics Institute (IGI), founded by Nobel laureate and CRISPR gene editing co-discoverer Jennifer Doudna, announced a new partnership to jointly develop cutting-edge genomic tools for addressing large-scale challenges in health and the environment.
Doudna founded the IGI in 2015 with the aim of translating the success of gene editing in the lab into practical solutions for large societal problems. Initially formed as a partnership between UC Berkeley and UC San Francisco with a focus on using CRISPR in human health, the IGI expanded to include sustainable agriculture and climate change applications of genome editing, adding UC Davis as a partner. UC San Diego is joining as the IGI’s fourth UC partner campus, combining research strengths in environmental and marine science, engineering and computer science, and biomedical and life sciences to develop the next generation of genome-editing tools and applications.
“I’m thrilled that the IGI is now partnering with UC San Diego,” said Doudna. “The mission of the IGI is to develop solutions that can not only scale to meet the biggest challenges in health and climate, but to make solutions that are accessible to those who need them most. UC San Diego helps us expand that real-world impact.”
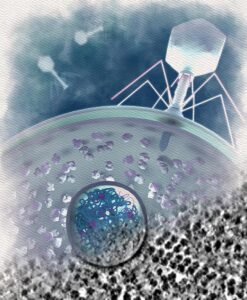
An artistic depiction of a jumbo phage infecting a bacterium. [Margot Riggi]
The relationship between UC San Diego and IGI research labs has been building over the past decade. For several years, the IGI has been collaborating with UC San Diego researchers Joe Pogliano, PhD, professor in the Department of Molecular Biology, and Kit Pogliano, PhD, dean and professor in the School of Biological Sciences, on applied microbiology projects. They have worked with UC Berkeley-based labs on developing new therapies focusing on “jumbo phage” for antibiotic-resistant bacterial infections as well as a novel defense strategy against viral infections.
In 2023, UC San Diego researchers were awarded $10 million by the Howard Hughes Medical Institute to explore the biomedical promise of jumbo phage as therapeutic agents. Also in 2023, the IGI received a $70 million gift through the Audacious Project to develop microbiome-editing tools and apply them to problems caused by microbes and microbiome imbalances, including livestock methane emissions and inflammatory diseases like asthma. Other areas of the effort focus on developing more efficient tools for genome editing across a wide breadth of microorganisms to expand the impact of this technology.
In the environmental arena, UC San Diego researchers have worked closely with UC Berkeley labs since 2018 to develop tools for combatting crop pests, managing disease-carrying mosquito populations, and developing safe protocols for environmental applications of genomic technologies.
“UC San Diego brings exceptional strengths across biological sciences, medicine, engineering, computation, environmental research, and ocean science that align powerfully with the IGI’s mission,” said Pogliano.
In addition to the current collaborations, IGI’s executive director Brad Ringeisen foresees multiple areas of synergy: “UC San Diego’s strengths in engineering, medical devices, environmental research, and the microbiome complement IGI’s current research areas, and allow us to expand our societal impact in new ways,” he said.
New joint projects of particular interest include interdisciplinary programs designed to bolster the climate resilience of our oceans and soils through innovative scalable solutions, and combining UC Berkeley’s biotechnology discovery engine with UC San Diego’s biomedical research and health system to improve the drug discovery pipeline for rapid translation across areas like antimicrobial resistance and neurodegenerative disease.
Background: Attention-deficit/hyperactivity disorder (ADHD) affects 6.3% of Chinese children, but only 10% are diagnosed, as diagnosis is hindered by low awareness and lack of culturally adapted, objective tools. Existing continuous performance tests are unimodal and lack validity. Objective: This study aimed to conduct an initial evaluation of the diagnostic discrimination of BOKE STARS (Sustained Task and Attention Response Screening), a culturally adapted bimodal continuous performance test, for distinguishing children with ADHD from typically developing children in a Chinese clinical setting. Methods: In this prospective, single-center diagnostic accuracy study with a case-control design, 100 children aged 6 to 12 years (n=50 with ADHD and n=50 controls) were recruited at Xinhua Hospital between January and May 2024. Parents completed the Swanson, Nolan, and Pelham Rating Scale–fourth version (SNAP-IV), and children completed the BOKE STARS assessment on a tablet device under standardized conditions. Group comparisons were conducted using independent-sample 2-tailed tests or Mann-Whitney tests, as appropriate. Receiver operating characteristic (ROC) curve analysis was performed in the full case-control sample to assess diagnostic discrimination. Sensitivity and specificity were reported descriptively across ROC-derived cutoffs; these cutoffs were not interpreted as clinically validated diagnostic thresholds. Secondary exploratory analyses included comparisons among ADHD subtypes and correlations between BOKE STARS indices and parent-reported SNAP-IV symptom severity scores. Results: Compared with controls, children with ADHD performed significantly worse on all major BOKE STARS indices, including errors of omission, errors of commission, reaction time, reaction time variability (RTV), discrimination prime, and total score. In the full case-control sample, the total score showed the strongest diagnostic discrimination (area under the ROC curve [AUC] 0.962, 95% CI 0.931-0.992), followed by RTV (AUC 0.919, 95% CI 0.867-0.971), errors of omission (AUC 0.884, 95% CI 0.818-0.950), and discrimination prime (AUC 0.819, 95% CI 0.737-0.900). Errors of commission (AUC 0.689, 95% CI 0.585-0.792) and reaction time (AUC 0.634, 95% CI 0.524-0.743) showed comparatively weaker discrimination. No significant differences were observed among ADHD subtypes. Several BOKE STARS indices were modestly correlated with SNAP-IV inattention and hyperactivity or impulsivity scores. Conclusions: BOKE STARS showed promising preliminary diagnostic discrimination for identifying Chinese children with ADHD in this case-control sample, with the total score and RTV showing the strongest discriminatory performance. However, because the case-control design artificially fixed the ratio of ADHD cases to controls, diagnostic performance estimates and exploratory cutoffs should be interpreted cautiously and should not be considered representative of real-world clinical diagnostic performance. BOKE STARS may serve as an adjunctive assessment tool to complement clinical interviews and caregiver-reported rating scales, but further external validation in larger and clinically heterogeneous populations is required before broader clinical implementation.
<img src="https://jmir-production.s3.us-east-2.amazonaws.com/thumbs/a352c65e649b80c4b66c3ed01598115e" />
Background: Dietary counseling is an essential complement to the growing use of glucagon-like peptide-1 receptor agonists (GLP-1 RAs) to achieve sustainable weight loss. Diverse patient needs, the demand for ongoing support, and limited resources underscore the potential of using digital support tools. Objective: This study aimed to evaluate the usability, treatment satisfaction, and weight effects of a personalized nutrition advisor (PNA), a prototype decision-support tool designed to facilitate personalized weight management counseling. Methods: We assessed usability, treatment satisfaction, and weight effects of a web-based PNA prototype dashboard designed to help dietitians deliver personalized remote dietary counseling in overweight adults (BMI ≥28 kg/m² at pharmacotherapy initiation) who had achieved ≥5% weight loss with GLP-1 RA therapy over 12-weeks. The PNA dashboard generated tailored nutritional recommendations to help participants achieve personalized weight loss goals based on an energy balance model that estimated daily caloric intake and nutritional quality using frequent body weight measurements, dietary logs, and physical activity data from a lifestyle-tracking app. To evaluate the PNA’s usability, we used a convergent parallel mixed-methods approach, combining a validated quantitative usability survey and qualitative focus-group interviews and feedback questionnaires with both dietitians and patients, alongside patient-reported satisfaction metrics for PNA-guided consultations (treatment satisfaction, general self-efficacy, and perceived health impact). Thematic analysis with a hybrid deductive-inductive methodology was applied to qualitative data, using 4 a priori themes derived from this study’s conceptual framework regarding prior expectations, perceived utility and satisfaction, usability challenges, and suggestions for clinical integration. Percent weight loss during the intervention was assessed as an exploratory outcome. Results: Among 78 participants (58/78, 74% women), on GLP-1 RA (mean weight loss of −13.3%, SD 6.7%, after 10, SD 5, months of treatment), between 3 and 5 remote nutrition consultations were delivered with PNA support. After the 3-month intervention period, weight loss was sustained in all participants (−0.2%, SD 2.5%), with 21% (16/78) suspending the GLP-1 RA due to drug shortages. Dietitians rated the PNA’s usability as moderate (62%) on the Healthcare Systems Usability Scale. Patients evaluated the perceived health impact of the PNA-assisted consultations at 19.1 (SD 3.5) of 25 on the user version of the Mobile Application Rating Scale. No significant differences were observed in patient-reported treatment satisfaction (=.78) or self-efficacy (=.57) before and after PNA-assisted care. Qualitative analysis identified convergence with quantitative findings across themes of usability, treatment satisfaction, and clinical integration, with divergence observed for self-efficacy and tracking motivation. Both patients and dietitians found the PNA valuable for generating actionable nutritional insights. Conclusions: While effective implementation of tools such as the PNA prototype demands dietitian training and workflow integration, they offer scalable, personalized nutrition or lifestyle guidance—as a therapeutic decision-support tool within weight loss interventions, with or without adjunct GLP-1 RA pharmacotherapy. Trial Registration: ClinicalTrials.gov NCT05997771; https://clinicaltrials.gov/study/NCT05997771
<img src="https://jmir-production.s3.us-east-2.amazonaws.com/thumbs/673e7709f46aa65c02e80d8ca5751306" />
Background: Intravenous drug incompatibility is a significant medication safety hazard, particularly in complex multidrug regimens. Traditional text-based, pairwise query methods are inefficient and impose a substantial cognitive load on clinicians. While network visualization has the potential to address these challenges, its application in drug compatibility queries remains underexplored. Objective: This study aimed to design, develop, and evaluate a novel drug compatibility query system based on a WeChat Mini Program. The system integrates diverse data sources and uses network visualization to present complex compatibility relationships. We sought to empirically assess its impact on efficiency and user experience. Methods: A preliminary crossover usability and efficiency evaluation was conducted. Phase 1 involved the construction of a drug compatibility knowledge base from authoritative handbooks and drug labels, and the development of the query system. Phase 2 comprised a system evaluation with 36 pharmacists, 6 physicians, and 5 nurses. The evaluation included a scenario-based task completion time analysis comparing the system (Mode A) with traditional print-based resources (Mode B), a quality assessment using the Mobile Application Rating Scale (MARS), and structured posttask user feedback to gather insights on user experience. Results: The query system demonstrated a substantial reduction in task completion time, with median time savings of 2.85 (IQR 1.98‐4.15) minutes, 5.45 (IQR 3.95‐7.20) minutes, and 31.2 (IQR 27.5‐35.1) minutes, respectively, in 3 scenarios with different complexity. The system received a high mean overall quality score of 3.88 (SD 0.35) on the MARS. The functionality dimension scored the highest (mean 4.21, SD 0.51), while engagement scored the lowest (mean 3.21, SD 0.62). Posttask structured feedback revealed five major areas of user feedback: (1) baseline experience and first impressions, (2) user experience with network visualization, (3) perceived efficiency and cognitive load, (4) trust and information quality, and (5) future application considerations. Users praised the system’s efficiency and intuitive design but expressed a strong need for transparent data sources and management advice to build trust. Conclusions: A query system based on network visualization demonstrates potential to support the efficiency of multidrug compatibility queries within this preliminary evaluation. It may mitigate cognitive load and offer an at-a-glance understanding of complex drug relationships. However, formal clinical accuracy validation remains a mandatory precondition before bedside clinical deployment is considered.
<img src="https://jmir-production.s3.us-east-2.amazonaws.com/thumbs/158e68d9d329ce892467e2b18898b00c" />
Duchenne muscular dystrophy (DMD) is a progressive, multisystem disease requiring long-term monitoring of respiratory, cardiac, and functional status. Advances in care have extended survival, increasing the need for continuous, coordinated management. In parallel, digital health technologies have enabled remote monitoring and data collection outside traditional clinical settings. This Viewpoint examines the role of device-based remote monitoring in DMD and argues that it should be understood as an emerging multisystem digital surveillance framework rather than a collection of isolated technologies. This Viewpoint is based on a synthesis of published literature on device-based remote monitoring and digital health technologies in DMD and experiences at our center. The aim was to outline the current clinical and technological landscape and support an interpretive perspective. Device-based monitoring in DMD encompasses a range of technologies, including home spirometry, ventilator-integrated telemonitoring, wearable activity sensors, cardiac rhythm monitoring, and interactive rehabilitation systems. These approaches enable longitudinal assessment of physiological and functional parameters in real-world settings. However, the current evidence base is heterogeneous and largely limited to feasibility studies, small cohorts, and extrapolated data. While data acquisition is technically feasible and increasingly available, integration into clinical workflows remains constrained by the lack of validated digital biomarkers, standardized monitoring frameworks, and interoperable data systems. Remote monitoring in DMD is evolving toward a connected, multisystem model of disease surveillance. Its clinical impact will depend on the validation of digital end points, development of decision support frameworks, and integration into multidisciplinary care pathways. Bridging the gap between data generation and clinical decision-making remains a key priority for future research and implementation. These findings support a shift from isolated technologies toward a coordinated, clinically integrated model of multisystem care in DMD.
<img src="https://jmir-production.s3.us-east-2.amazonaws.com/thumbs/3f71d59c414c9e0a386a2acb7220e948" />
Background: Adolescents and young adults seeking contraceptive care face many considerations related to differences in contraceptive indications and knowledge, which are often overlooked and can lead to contraceptive nonadherence or nonuse as well as adverse health outcomes. Objective: This study aimed to develop a digital decision aid that meets the contraceptive decisional needs of adolescents and young adults from diverse backgrounds. Methods: We developed a web-based decision aid using a user-centered design framework and the International Patient Decision Aid Standards. The design and development process was informed by a literature review and consultations with scientific experts, health informatics specialists, clinicians experienced in adolescent reproductive health, and a diverse group of adolescent and young adult advisors. We gathered feedback on the decision aid’s content and functionality from clinicians, adolescents, and young adult stakeholders during focus group interviews conducted across 2 user testing cycles. Each focus group was recorded and transcribed, and the data were analyzed using a focus group guide to identify key attributes, patterns, and perspectives among users. Two qualitative researchers used rapid qualitative analysis to explore and summarize findings across 4 key domains, which contributed to the refinement of the decision aid content and the improvement of its functionality. Results: Twenty-four clinicians, adolescents, and young adult participants from diverse backgrounds shared their perspectives on the decision aid’s content, relevance, design, and usability across 2 user testing cycles conducted from February 2023 to June 2024. The decision aid includes a survey, a decision algorithm that generates a summary of contraceptive method recommendations, infographics, and a health care provider summary view. The decision algorithm applies a weighted scoring system ranging from +1 or −1 to +10 or −10 for each method, reflecting the user’s primary indication for seeking contraception, contraceptive use preferences, and relevant health history. Conclusions: This approach allowed us to capture rich perspectives from a diverse group of stakeholders that accounted for the unique contraceptive decision-making needs of adolescents and young adults, resulting in a functional, youth-informed decision aid prototype, <i>MyPlanMyChoice</i>, ready for pilot and feasibility evaluation in a clinical setting.
Background: Depression carries the highest burden of mental health–related disability in the United States. Approximately 13% of military veterans report elevated rates of depression. Despite the availability of evidence-based treatments for depression, nearly 50% of veterans in need of mental health care remain untreated. Internet-based interventions show promise in reducing this gap; however, there are currently no standard self-guided internet-based interventions for depressive symptoms in veterans. Deprexis is one such intervention that leverages cognitive behavioral therapy to target depressive symptoms. Objective: This pilot study evaluated the feasibility, acceptability, and preliminary effectiveness of Deprexis, a fully self-guided internet-based intervention for depression, in US military veterans with mild to severe depressive symptoms. Methods: This open-label pilot trial recruited 19 veterans with mild to severe depression (mean age 55.5, SD 8.2 y; baseline Quick Inventory of Depressive Symptomatology—Self-Report [QIDS-SR]: mean 16.2, SD 4.1) for an 8-week course of Deprexis, with self-report assessments at baseline, posttreatment (8 wk), and follow-up (16 wk). Primary outcomes included depressive symptoms (QIDS-SR), functional disability (World Health Organization Disability Assessment Schedule 2.0), and symptom-related disability (Sheehan Disability Scale). Feasibility was assessed through recruitment and retention rates, and acceptability was measured using validated questionnaires (Credibility and Expectancy Questionnaire and Client Satisfaction Questionnaire). Multilevel models examined change over time, with effect sizes calculated using pooled SDs from unconditional models. Results: Recruitment and retention targets were met, with 15 out of 19 (79%) participants meeting the adherence criteria (ie, ≥60 min of active program use). Of these, 14 participants completed posttreatment questionnaires and were included in the completer analyses. The program received a positive acceptability rating: of the 18 participants who completed follow-up assessments, 78% (n=14) rated services as good or excellent and 72% (n=13) were satisfied with the amount of help received. No safety concerns were reported. Among completers (n=14), QIDS-SR scores decreased from baseline to posttreatment (estimate −2.22, SE 1.44; =.14; =−0.54, 95% CI −1.07 to 0.13) and follow-up (estimate −2.85, SE 1.19; =.02; =−0.70, 95% CI −1.21 to −0.08) with moderate-to-large effect sizes. Effect sizes were similar in the total sample. Functioning (World Health Organization Disability Assessment Schedule 2.0) improved among completers at follow-up (estimate −8.09, SE 3.80; =.045; =−0.41, 95% CI −0.96 to −0.05). Disability (Sheehan Disability Scale) did not significantly improve from baseline to posttreatment or follow-up. Conclusions: This pilot trial demonstrates that Deprexis is feasible and acceptable for veterans with mild to severe depression, with preliminary evidence of effectiveness for depressive symptoms. The delayed emergence of functional improvements and sustained gains at follow-up support the potential of this scalable intervention. The results provide a strong foundation for the ongoing randomized controlled trial. Trial Registration: ClinicalTrials.gov NCT06217198; https://clinicaltrials.gov/study/NCT06217198 International Registered Report Identifier (IRRID): RR2-10.2196/59119
<img src="https://jmir-production.s3.us-east-2.amazonaws.com/thumbs/70826d4d70665042dcb7552593cb44c1" />
Researchers from Keio University School of Medicine and Keio University Regenerative Medicine Research Center in Japan transplanted neural stem/progenitor cells derived from induced pluripotent stem cells (iPSCs) into the injured spinal cords of four men with recent, complete cervical spinal cord injuries. The first-in-human Phase I study, published in Nature Medicine, primarily evaluated safety, following participants for up to four years after treatment.
Spinal cord injury affects more than 20 million people worldwide and often results in permanent paralysis because the adult spinal cord has only limited capacity to regenerate. Current treatments—including surgery and rehabilitation—can stabilize the injury and maximize remaining function but cannot rebuild the damaged neural circuits responsible for movement and sensation.
The transplanted cells were manufactured from clinical-grade iPSCs under strict quality controls before being differentiated into neural stem/progenitor cells. Approximately two million cells were injected directly into each patient’s spinal cord injury site two to four weeks after injury while patients received temporary immunosuppressive therapy to reduce the risk of rejection.
The trial met its primary objective. Researchers observed no tumor formation, abnormal cell growth, or other serious complications attributable to the transplanted cells during the initial 52-week study period or the subsequent long-term follow-up. Imaging studies likewise revealed no evidence of graft-related abnormalities, addressing one of the field’s greatest concerns regarding therapies derived from pluripotent stem cells.
Although safety was the principal endpoint, investigators also tracked neurological recovery. All four participants showed improvements in motor function, and two improved enough to advance from complete paralysis (American Spinal Injury Association Impairment Scale grade A) to grades C or D, indicating recovery of some voluntary movement below the injury level. Median motor scores improved by 13 points after one year, exceeding the recovery typically observed in a comparable historical patient registry, although the researchers caution that the small, uncontrolled study cannot establish that the stem cell treatment caused these gains.
The encouraging results build on years of preclinical research showing that transplanted neural stem cells can differentiate into neurons and supporting cells, promote remyelination, stimulate regrowth of damaged nerve fibers, and release molecules that support tissue repair. Animal studies have also suggested that the transplanted neurons can integrate into existing spinal cord circuits, although such integration cannot yet be directly confirmed in patients.
The investigators emphasize that many questions remain before the therapy could become a standard treatment. The study enrolled only four participants, lacked a placebo control, and included only men with recent cervical spinal cord injuries. Larger randomized clinical trials will be needed to determine whether the treatment consistently improves neurological recovery and to identify which patients are most likely to benefit. Researchers also plan to continue monitoring participants to assess the long-term safety of the transplanted cells.
Even with those caveats, the findings represent a significant advance for regenerative medicine. Rather than demonstrating a cure for paralysis, the study establishes that carefully manufactured iPSC-derived neural stem cells can be transplanted into the human spinal cord without the serious safety issues that have long challenged the field. That achievement provides a critical foundation for the next generation of clinical trials aimed at determining whether stem cell therapy can ultimately restore function after devastating spinal cord injuries.
Having a common birth complication such as preterm birth, preeclampsia, high blood pressure and gestational diabetes puts women at increased risk of developing peripheral artery disease in later life.
As reported in PLOS Medicine, all five of the common complications listed were associated with an increased risk for peripheral artery disease, a form of atherosclerosis in the legs, up to 46 years after giving birth in a large Swedish study.
Overall, women with gestational diabetes had almost four-times higher risk of developing peripheral artery disease than women who had a healthy pregnancy with preeclampsia, high maternal blood pressure, preterm birth or small for gestational age babies increasing risk 1.3–1.7-fold.
“Peripheral artery disease affects more than 230 million people worldwide and is a strong predictor of future stroke, ischemic heart disease, and premature mortality,” write Casey Crump, MD, PhD, an epidemiologist and family physician at McGovern Medical School, and colleagues.
“Despite its high prevalence and clinical importance, it is understudied compared with other cardiovascular diseases.”
Pregnancy complications such as gestational diabetes and preeclampsia are known to increase the risk of other types of cardiovascular disease so Crump and team carried out a study to assess if this was also the case for peripheral artery disease.
The team drew on Swedish national birth and health registries to follow more than 2.2 million women who had single‑baby pregnancies between 1973 and 2015. They focused on the five common birth complications and tracked new diagnoses of peripheral artery disease from hospital, specialist clinic, and primary care records for up to 46 years after childbirth.
The researchers compared women with and without these complications while accounting for age, education, income, smoking, weight, and existing conditions like hypertension or diabetes. The also compared sisters to check whether shared genes or family lifestyle could fully explain the patterns they saw.
Overall, 13,211 women developed peripheral artery disease, mostly in their early 60s. All the complications were linked to higher risk of arterial disease, with the association becoming stronger with age. Experiencing more than one complication also increased risk further and women with three or more had around three times higher risk of peripheral artery disease in later life than women with none. The research also showed links were not likely to be genetic or related to a shared upbringing.
“Women who experience an adverse pregnancy outcome need early preventive actions and long-term clinical follow-up to reduce their risk for peripheral artery disease and other associated cardiovascular diseases,” write the authors.